
A superbill is an itemized statement of services that a provider gives to a patient, who then submits it with their insurer’s own claim form or through the insurer’s member portal. A CMS-1500 is the standardized professional claim form that providers or billers typically submit directly to insurers. Both carry largely the same information, but they serve different steps in the reimbursement process and are sent by different people.
This guide explains when you need each one, whether a superbill counts as a claim, and how every superbill field maps to a CMS-1500 box.
What is a superbill?
A superbill is a detailed receipt for healthcare services, built to support an insurance reimbursement request. It lists the provider’s identifiers, the patient’s insurance details, diagnosis codes, and each service with its date, CPT code and fee. Out-of-network and private-pay providers give superbills to clients so the clients can request reimbursement from their insurer or document expenses for an HSA or FSA.
There is no single official superbill format. What matters is that it contains the data elements insurers need. Our guide to what a superbill is covers the basics.
What is the CMS-1500 form?
The CMS-1500 (version 02/12) is the standard paper claim form for professional services in the US. It is maintained by the National Uniform Claim Committee and accepted by Medicare, Medicaid and most commercial payers. Its electronic equivalent is the 837P transaction, which is how most in-network claims are actually sent today.
Key features:
- Fixed layout. Every box has a defined purpose and position, so insurers can scan and process it consistently.
- Box 21 holds up to 12 ICD-10 diagnosis codes, lettered A through L.
- Box 24 holds the service lines, with room for six lines per form.
- Paper submissions generally require the official red-ink form so it can be read by scanning equipment; photocopies and home-printed versions are often rejected.
Superbill vs CMS-1500: side-by-side comparison
| Superbill | CMS-1500 | |
|---|---|---|
| What it is | Itemized statement of services | Standardized claim form |
| Who prepares it | Provider or practice | Provider, practice or biller |
| Who usually submits it | The patient | The provider or biller |
| Format | Flexible; no single official layout | Fixed, standardized layout |
| How it’s sent | Attached to the insurer’s member claim form or uploaded to a member portal | Electronically (837P) or on the official paper form |
| Typical use | Out-of-network reimbursement, HSA/FSA documentation | In-network billing, courtesy billing, Medicare and Medicaid |
| Payment goes to | Usually the patient | Usually the provider, if benefits are assigned |
Is a superbill a claim?
No. A superbill is supporting documentation, not a claim. The claim is the request for payment, and with out-of-network reimbursement it is the patient who files it, using:
- The insurer’s member reimbursement or claim form, with the superbill attached, or
- The insurer’s online member portal or app, where the superbill is uploaded
The insurer then reads the superbill and enters its details into its claim system. That is why superbills that mirror CMS-1500 data elements tend to process faster: the insurer finds every field it needs in a familiar form. Our step-by-step guide on how to submit a superbill to insurance walks through the process from the client’s side.
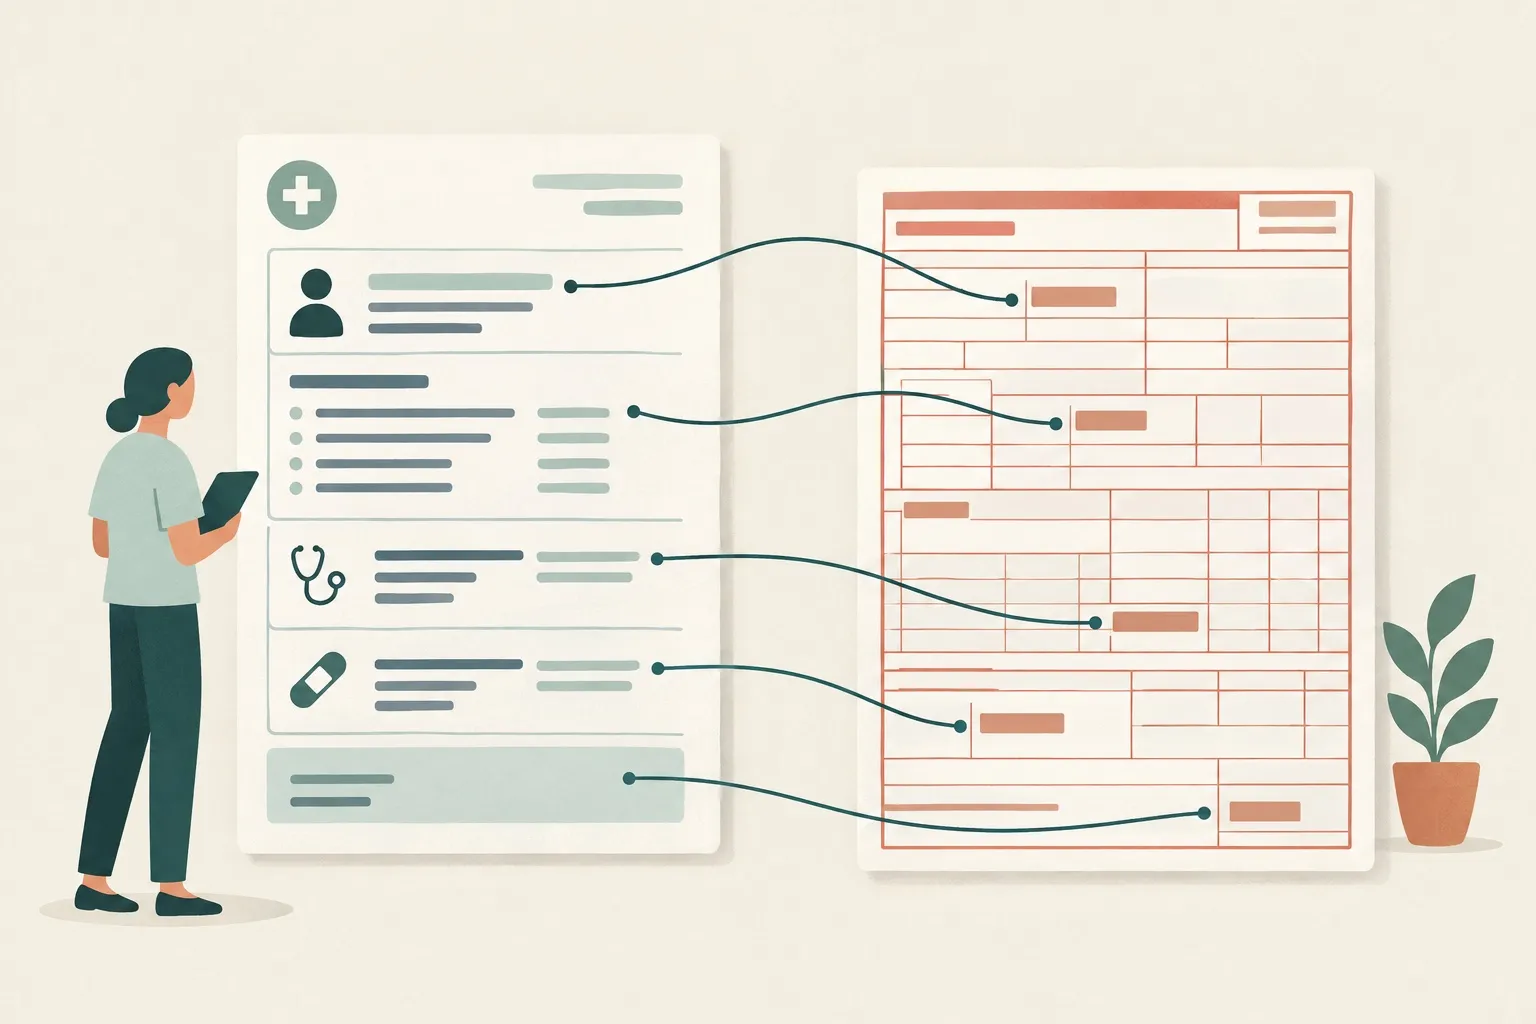
How superbill fields map to CMS-1500 boxes
If you have ever wondered why superbills include certain fields, this table shows where each one ends up on a CMS-1500.
| Superbill field | CMS-1500 location |
|---|---|
| Patient name | Box 2 |
| Patient date of birth | Box 3 |
| Insurance member ID | Box 1a |
| Insurance carrier | Carrier block at the top of the form |
| Group number, patient address | Patient and insured information sections |
| Diagnosis codes (A–L) | Box 21 |
| Date of service | Box 24A |
| Place of service (POS) | Box 24B |
| CPT code and modifier | Box 24D |
| Diagnosis pointer | Box 24E |
| Fee (charges) | Box 24F |
| Units | Box 24G |
| Rendering provider NPI | Box 24J |
| Tax ID / EIN | Box 25 |
| Provider signature | Box 31 |
| Practice address where services were provided | Box 32 |
| Billing provider name, address and phone | Box 33 |
A few notes on the mapping:
- Diagnosis pointer. On a CMS-1500, Box 24E does not hold the ICD-10 code itself; it holds the letter (A–L) that points to a code in Box 21. Good superbills use the same lettered system, so each service line points to the diagnosis it treats.
- POS. Telehealth sessions need the correct POS for the payer, often 10 when the patient is at home or 02 when they are elsewhere. See our telehealth place of service codes guide.
- Box 24C is an emergency indicator. It is rarely used for outpatient therapy or similar services, so superbills generally leave it out.
- Amount paid also has a place on the CMS-1500. Superbills show the amount paid and remaining balance so the insurer can see that the patient has already paid the provider, which matters when reimbursement is sent to the patient.
What goes in CMS-1500 Box 24?
Box 24 is where the services live. Each of its six lines describes one service:
- 24A — date(s) of service
- 24B — place of service
- 24C — emergency indicator
- 24D — CPT or HCPCS code, plus up to four modifiers
- 24E — diagnosis pointer (letters referring to Box 21)
- 24F — charges
- 24G — days or units
- 24J — rendering provider NPI
If a patient has more than six services in a billing period, the provider uses additional forms. A superbill has no fixed line limit, but it should include the same per-line details.

When do you need a superbill vs a CMS-1500?
| Situation | What you typically need |
|---|---|
| You are out-of-network and the client files their own claim | Superbill |
| Client wants to document expenses for an HSA or FSA | Superbill or itemized receipt |
| You are in-network with the client’s plan | Claim from the provider (usually electronic 837P; paper CMS-1500 if the payer allows) |
| You are out-of-network but offer courtesy billing | CMS-1500 or electronic claim from the provider |
| Client has Medicare | Claim from an enrolled provider; superbills generally don’t apply |
| Client’s insurer accepts member-submitted CMS-1500s | Either, per the insurer’s instructions |
For most private-pay therapists, dietitians, chiropractors and similar practices, the answer is a superbill. That keeps you out of the billing workflow, and the client deals with their insurer directly. If you want to understand the client’s side, our guide to out-of-network reimbursement for therapy explains how benefits, deductibles and allowed amounts work. For tax-advantaged accounts, see using a superbill for HSA and FSA.
What about Medicare?
Medicare works differently. Providers enrolled in Medicare are generally required to submit claims for covered services themselves, so patients typically do not file their own claims with a superbill. And if a provider has opted out of Medicare, Medicare will not reimburse the beneficiary for that provider’s services. Superbills are mainly a commercial-insurance tool.
Can you convert a superbill into a CMS-1500?
Yes, in the sense that a complete superbill contains nearly everything a biller needs to fill out a CMS-1500. If you later decide to offer courtesy billing, or a client’s insurer asks for a CMS-1500, the data can be transferred box by box using the mapping table above. The superbill itself is not a substitute for the official form when a payer requires one.
Common mistakes with superbills and claim forms
Most delays come from missing data rather than the choice of document. Watch for these:
- Lumping sessions together. A line that says “8 sessions in October” with one total is hard for an insurer to process. Every service needs its own line with a date, code and fee, exactly as Box 24 would require.
- Diagnosis codes with no pointers. Listing ICD-10 codes at the top without linking each service line to one leaves the insurer guessing which condition each service treated.
- Missing provider identifiers. An NPI and Tax ID are expected on both documents. A superbill without them often comes back with a request for more information.
- Discounted or net fees. List your full charge on each line and show payments separately. Insurers apply their own allowed amount to the full charge.
- Photocopied or home-printed CMS-1500s sent to payers that require the official red-ink form.
- Sending a superbill alone when the insurer requires its own member claim form on top. Clients should check the insurer’s instructions first.
- Submitting a superbill for a Medicare visit, which generally won’t work for the reasons above.
Make a superbill that maps cleanly to the CMS-1500
The free superbill generator is built around the same data elements as the CMS-1500: up to 12 diagnoses lettered A–L, service lines with date, CPT, modifier, POS, diagnosis pointer, units and fee, plus NPI and Tax ID fields with a checklist that flags anything insurers usually require. It runs entirely in your browser, and nothing is uploaded. Browse the superbill templates, such as the therapist superbill template, to start with codes for your profession already loaded.
FAQ
Is a superbill the same as an insurance claim?
No. A superbill is an itemized statement of services that a patient attaches to a claim they file with their insurer. The claim itself is either the insurer's member claim form, a portal submission, or a standardized claim such as the CMS-1500 or its electronic version. The superbill supplies the details the insurer needs to process that claim.
Can a patient submit a CMS-1500 instead of a superbill?
Some insurers will accept a completed CMS-1500 from a member, but most ask members to use their own reimbursement form or online portal with an itemized bill attached. Check the insurer's member reimbursement instructions before choosing a format.
What goes in Box 24 of the CMS-1500?
Box 24 holds the service lines. For each line you enter the date of service in 24A, place of service in 24B, the emergency indicator in 24C, the CPT or HCPCS code and modifiers in 24D, the diagnosis pointer in 24E, charges in 24F, days or units in 24G, and the rendering provider's NPI in 24J.
Do out-of-network providers need to use the CMS-1500?
Not usually. Out-of-network providers who do not bill insurers directly typically give clients a superbill, and the client files the claim. A CMS-1500 is needed when the provider, or a biller, submits the claim on the patient's behalf, such as for courtesy billing.
Does Medicare accept superbills from patients?
Generally no. Medicare-enrolled providers are typically required to submit claims for covered services themselves, and Medicare does not reimburse beneficiaries for services from providers who have opted out. Superbills are mainly used with commercial insurance plans.


